
According to the European Association of Urology (EAU) guidelines, this patient has an intermediate-risk tumour because of recurrent disease [1]. The individual 5-year risk of recurrence based on the EORTC risk tables is 46% [2]. According to the new EAU risk tables, the probability of progression for this patient (not BCG treated) is 4.9% at 5 years [1]. In order not to miss any recurrences, regular follow-up of this patient is advocated. Chiefly, any high-grade recurrence needs to be detected as early as possible given its correlation with a higher risk to progress to muscle-invasive disease.
The EAU guidelines recommend regular cystoscopy for the follow-up of TaT1 tumours and CIS. The frequency of cystoscopies depends on the risk group classification of the patient, which is based on their probability of progression to muscle-invasive disease. For patients with intermediate-risk Ta tumours, the guidelines recommend an individualised follow-up schedule somewhere in between the proposed follow-up schedules for low- and high-risk patients [1].
Cystoscopy follow-up scheme according to the EAU guidelines [1]
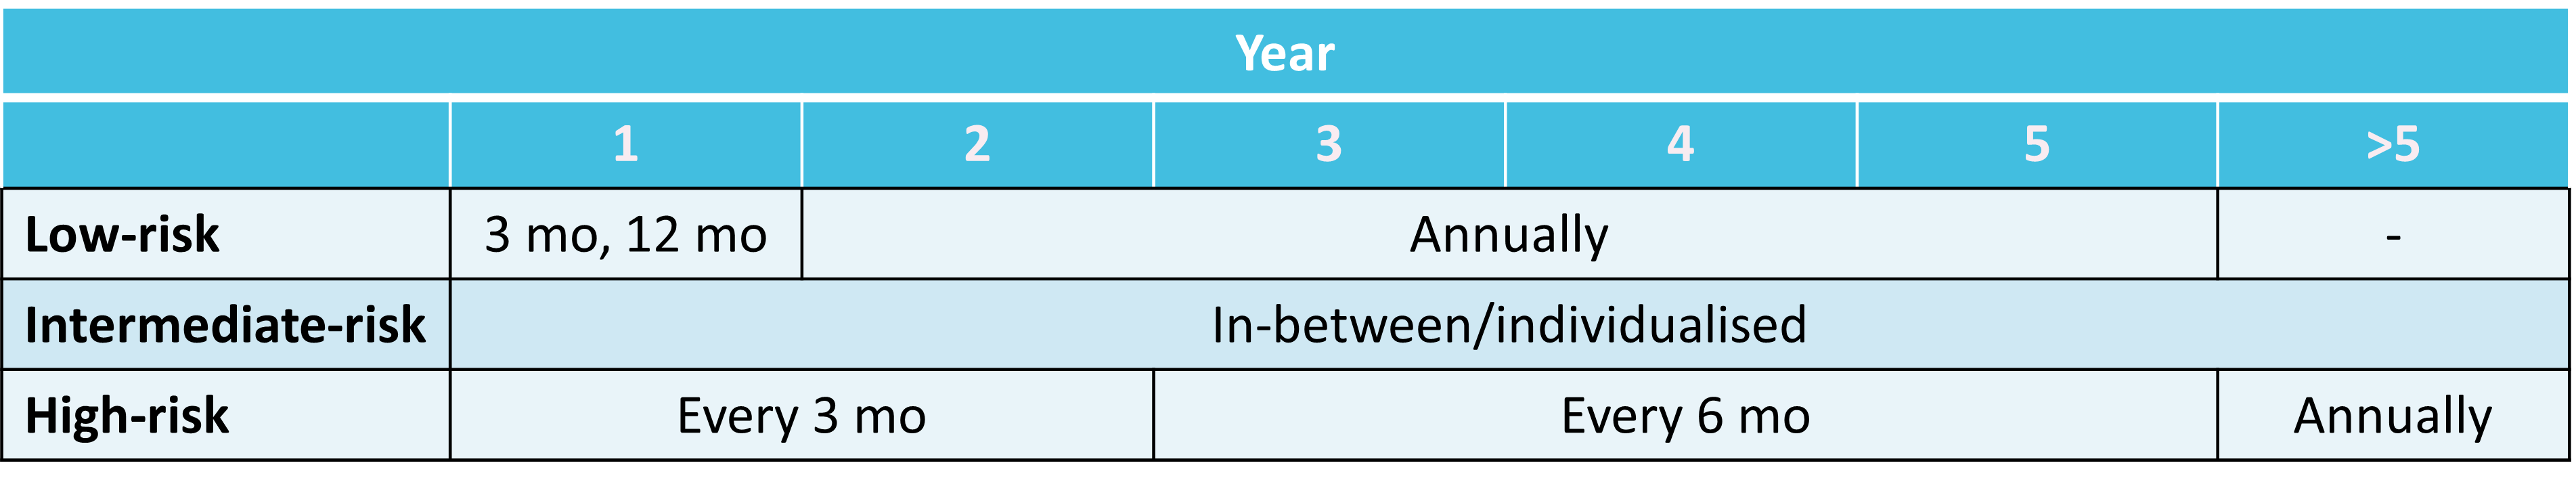
The follow-up schedule recommendations with cystoscopy are weak as they are not evidence-based. We don’t want to miss recurrences in our patients and therefore we often perform cystoscopies even more frequently than necessary according to the guidelines. A recent study reported a cystoscopy excess in 75% of low-risk NMIBC patients, comparing guideline recommendations to the frequency of follow-up cystoscopies in daily practice [3]. A similar scenario may apply to the intermediate-risk category given the absence of high-grade disease.
However, frequent cystoscopies pose a significant burden for the patient and the healthcare system, and cystoscopies are not 100% accurate to detect disease recurrence. The sensitivity for detecting papillary tumours ranges from 75 to 84% and is even lower for detecting CIS (61-62%), meaning high-grade lesions are often missed [4,5].
Urinary biomarkers could be a reliable and easy way to detect and rule out high-grade bladder cancer recurrence. Bladder cancer biomarker tests with a high sensitivity and a high negative predictive value (NPV) for high-grade tumours could be safely and effectively used to rule out high-grade recurrences. Less importantly, high specificity would ensure low rates of false positives, thereby avoiding as many of the negative cystoscopies as possible.
The EAU guidelines [1] acknowledge that there are promising novel urinary biomarkers with very high NPV, that have been tested in prospective, multi-centre studies [6-9].
Outcomes of prospective studies of new urinary markers for bladder cancer surveillance
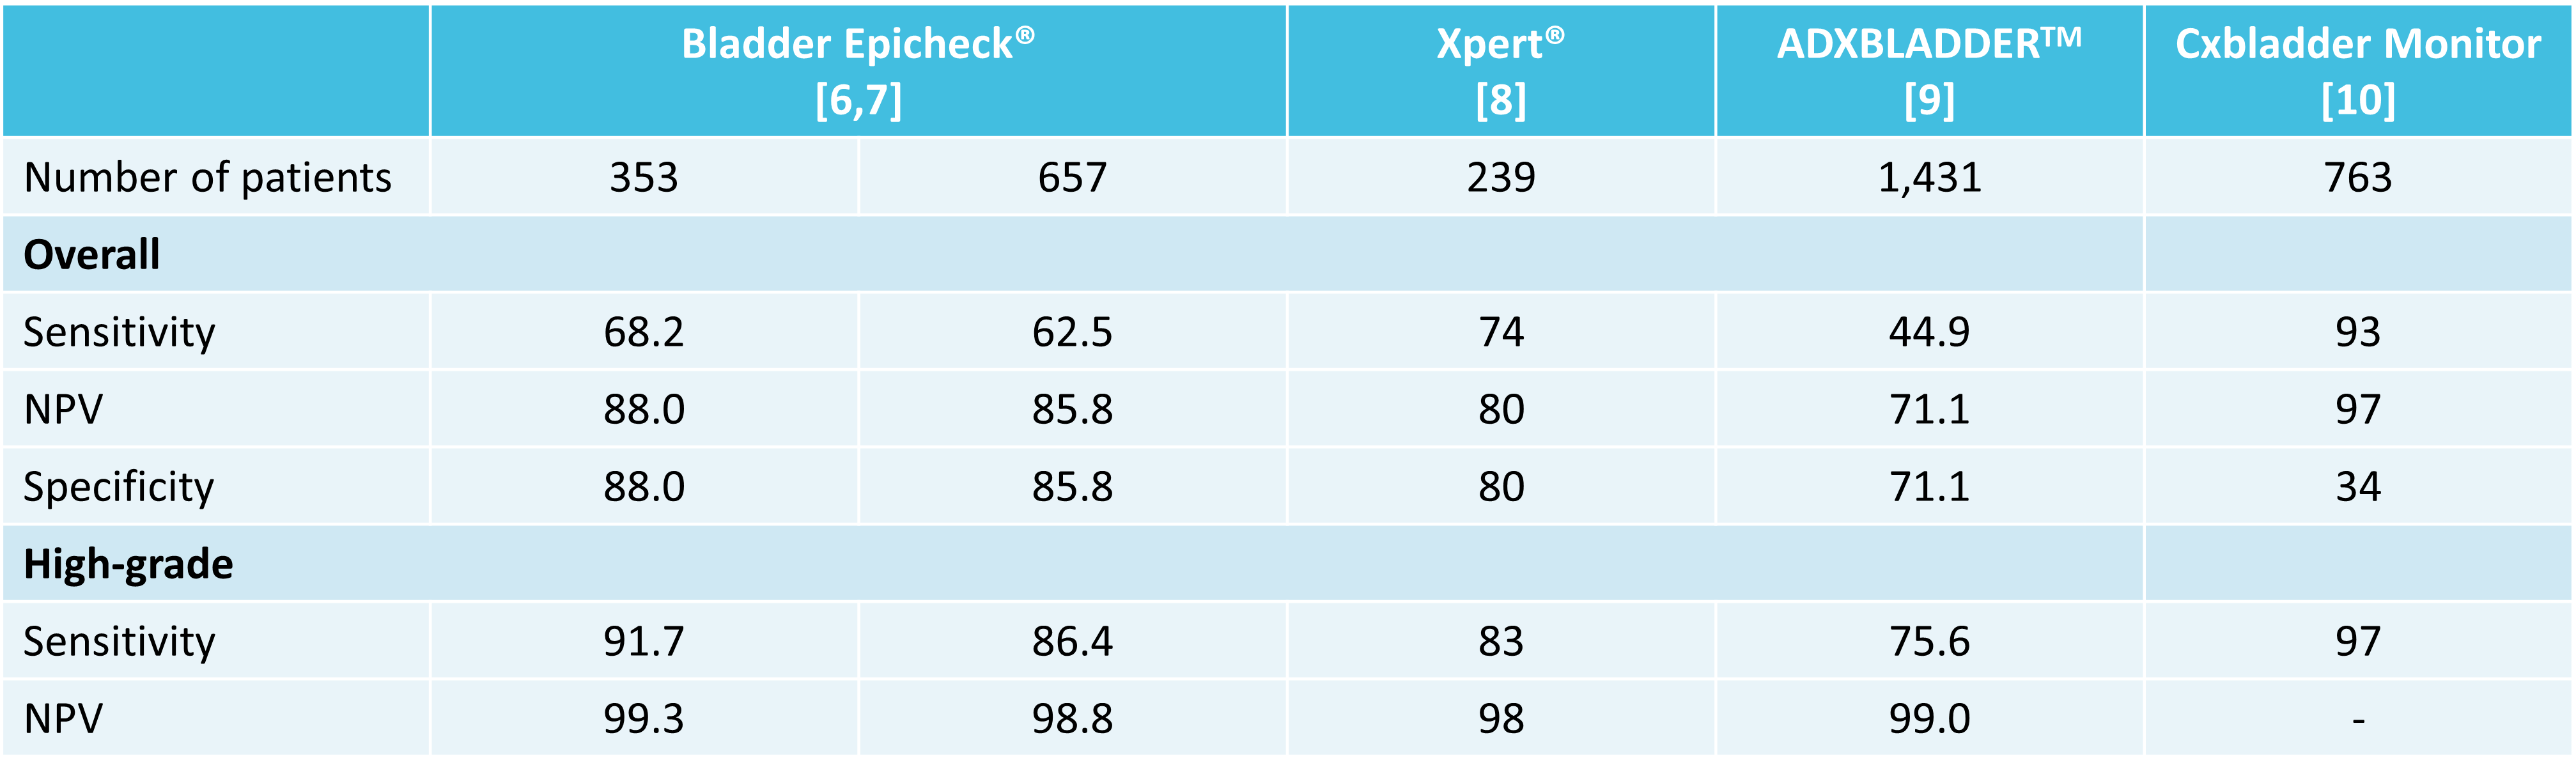
While current guidelines state that no urinary marker can replace cystoscopy during follow-up or lower cystoscopy frequency in a routine fashion, the new 2021 EAU guidelines added that a urinary marker may be a mode of surveillance in patients initially diagnosed with Ta low-grade bladder cancer in case cystoscopy is not possible or refused by the patient [1].
Given that this patient wants to avoid cystoscopies as much as possible, due to the associated burden and anxiety, alternating cystoscopies with a biomarker test would ensure this patient a prompt detection of a high-grade recurrence. This is crucial for early identification of the small proportion of recurrences prone to undergo progression. On the other side, overlooking a tiny low-grade recurrence (might be left undetected by a biomarker and unspotted by a bladder ultrasound) would not represent a significant risk to the patient, given that low-grade recurrent NMIBC can be safely treated with active surveillance. This will reduce the frequency of invasive procedures and hospital visits substantially, while the patient remains reassured that high-grade tumour recurrences will be detected early.
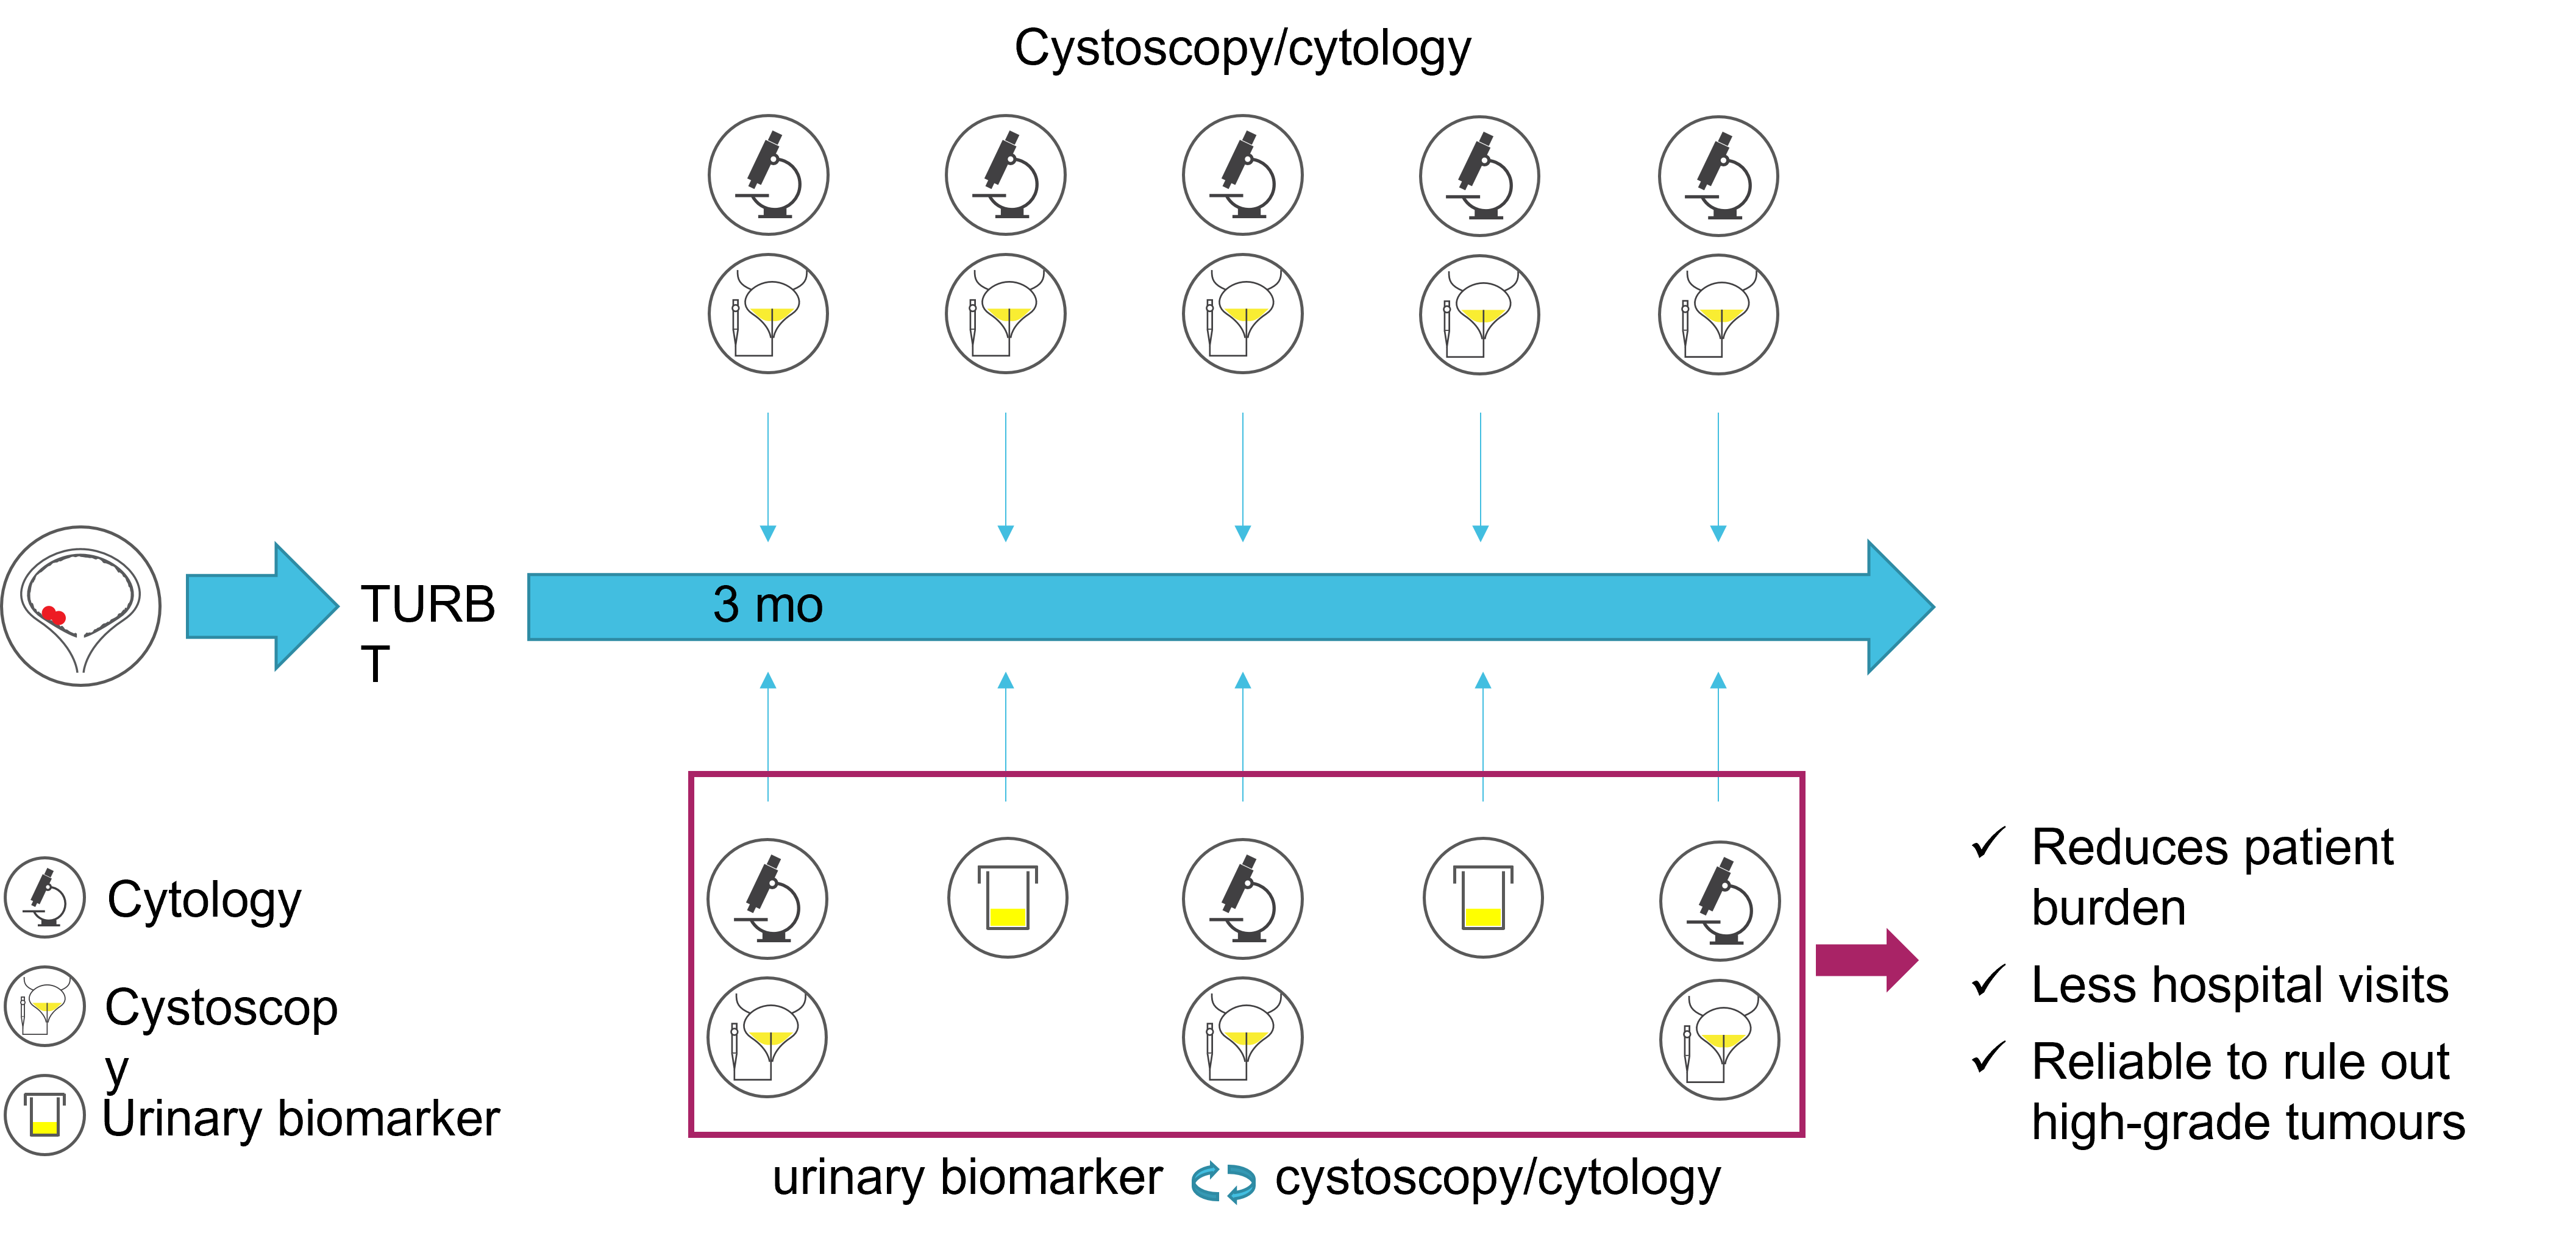
In light of the new EAU 2021 guidelines, patients with low-grade Ta tumours, such as Jimmy, should be properly informed on urinary markers, as they have the ability to reduce patient burden without compromising an early detection of high-grade recurrences. This will help to optimise and individualise the follow-up schedule for each patient, in accordance with the patient’s wishes.